



Geoff’s Narration
The GIST
The Second Generation Makes Progress…

Clinical trials are getting smarter. BioVie produced an “exploratory” trial which included an extensive assessment of possible biomarkers.
Last year, UCSF researcher and LIINC cofounder Dr. Michael Peluso compared first- and second-generation long-COVID clinical trials. The first-generation trials relied on educated guesses, were largely aimed at symptom relief, and mostly failed. That was no surprise to people with ME/CFS whose experience is that the standard batch of drugs often provides modest relief at best.
The second generation of drug trials tends to be smarter, more focused on the physiological aspects of long COVID, often attempts to uncover biomarkers, and are better engineered overall. Some are also considerably larger than the trials we in the ME/CFS community are used to.
Take BioVie’s long-COVID Bezisterim trial. The $13 million, 12-week, 208-person trial cost about as much as the entire NIH funding for ME/CFS last year. After the uber-conservative RECOVER initiative rather predictably turned down the opportunity to test a brand new drug (and bombed on all its treatment trials thus far), the Dept. of Defense took a leap and funded it – and, lo and behold, we have the best results of any drug trial thus far.

THE GIST
-

BioVie used this trial to identify subsets it could target in a larger, phase 3 trial.
Bezisterim is different. A new drug that has not been FDA-approved for any disease, Bezisterim reaches way up in a core inflammatory pathway to turn down inflammation – not just in the body but in the brain as well.
- BioVie, its manufacturer, scored when it secured a $13 million Department of Defense grant to test the drug in over 200 long-COVID patients.
- This trial was a little different than most. Acknowledging that long COVID is a highly heterogeneous disease, BioVie didn’t aim for a single endpoint; instead, it assessed 22 symptomatic endpoints. It also included over 400 biomarkers.
- The goal of the 12-week study was not simply to prove that Bezisterim helped people with long COVID, but to identify a subset of long-COVID patients likely to respond well in the next, larger drug trial BioVie hopes to hold.
- BioVie just announced the “topline” results; i.e., the most basic statistical findings from the trial.
- Given the heterogeneity in long COVID, it was not particularly surprising to see that when the entire long-COVID group was assessed, the drug failed to significantly affect any of the 22 symptomatic endpoints. That suggested that the drug would probably not be helpful for the long-COVID population at large.
- When the patients were divided up into more severe fatigue, more severe PEM, and more severe cognitive issues, though, things changed. This time the drug produced moderate “treatment effects” in symptoms like fatigue, PEM, cognition, global health, etc.
- Treatment effects refer to how likely a drug is to help a patient. In this case, when given to a patient, Bezisterim was moderately likely to help. We don’t know, however, how much the drug moved the needle on fatigue, or PEM, or other symptoms.
- It appeared that the sicker the long-COVID patient was, the better the drug did, and, in fact, Bezisterim produced similar findings in a Parkinson’s study.
- People involved in the study were happy with the results. Cuong Do, president and chief executive officer of BioVie, stated, “To my knowledge, this is the first time a drug candidate has shown the ability to help patients improve across these persistent long COVID symptoms.”
- Michael Peluso, a UCSF long-COVID researcher, stated: “There have been, at this point, a few dozen Long COVID trials of other agents, and really none of those have had results that are as consistent and as compelling as what I’m seeing here.”
- They are both correct. While the results we have suggest the drug is having a moderate effect, its ability to do so across multiple symptom domains seems notable – particularly with respect to past long-COVID trials.
- The really interesting question for me is what happens when BioVie adds in the biomarker results. Will it be able to identify an inflammatory subset that benefited significantly?
- Showing that tamping down an inflammatory marker led to significant improvements could be a game-changer not just for BioVie but for the long-COVID field as well, as it could compel other drug companies to take a chance on long COVID. (Lots of anti-inflammatory drugs are out there.)
- All 12 of BioVie’s advisory board counseled moving forward with a phase III drug trial and BioVie is in discussions with the FDA about that.

Support Health Rising and Keep the Information Flowing!
Health Rising is not a 501 c (3) non-profit
Interesting Drug!
Bezisterim, a newer drug, is not FDA-approved for any disease and is currently being assessed in three diseases: long COVID, early Parkinson’s, and Alzheimer’s.
It doesn’t fit common drug categories. Listed as an “anti-inflammatory and insulin sensitizing drug”, it has such wide-ranging effects that it could fit into several drug categories, including antiviral, nootropic, anti-dementia, antihyperglycaemic, and antiparkinsonian.
Bezisterim attempts to turn off or calm down a core inflammatory pathway called TLR-4. Once TLR4 senses a danger signal, it activates downstream inflammatory pathways such as ERK and NF-kB. These pathways then produce a broad array of inflammatory products (IL-1, IL-6, IL-8, TNF-α) of which TNF-α may be the most prominent.
Instead of suppressing the immune system as many drugs do, BioVie believes Bezisterim re-regulates – a potentially important factor.
BioVie believes Bezisterim’s superpower comes from its ability to rein in the low-grade inflammation produced by TNF-α. They believe that low-grade inflammation contributes to everything from insulin resistance, to production of the tau protein found in Alzheimer’s, to aging.
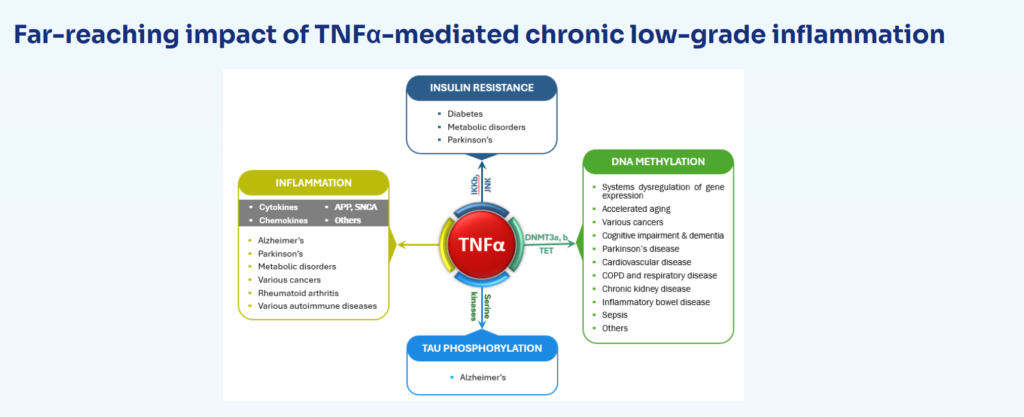
TNFα – the key driver of chronic low-grade inflammation?
Indeed, some researchers believe the inflammation in post-infectious diseases like long COVID and ME/CFS is maintained by a vicious circle caused by a chronically turned-on TLR4 pathway (TLR4 → NF‑κB → TNF‑α).
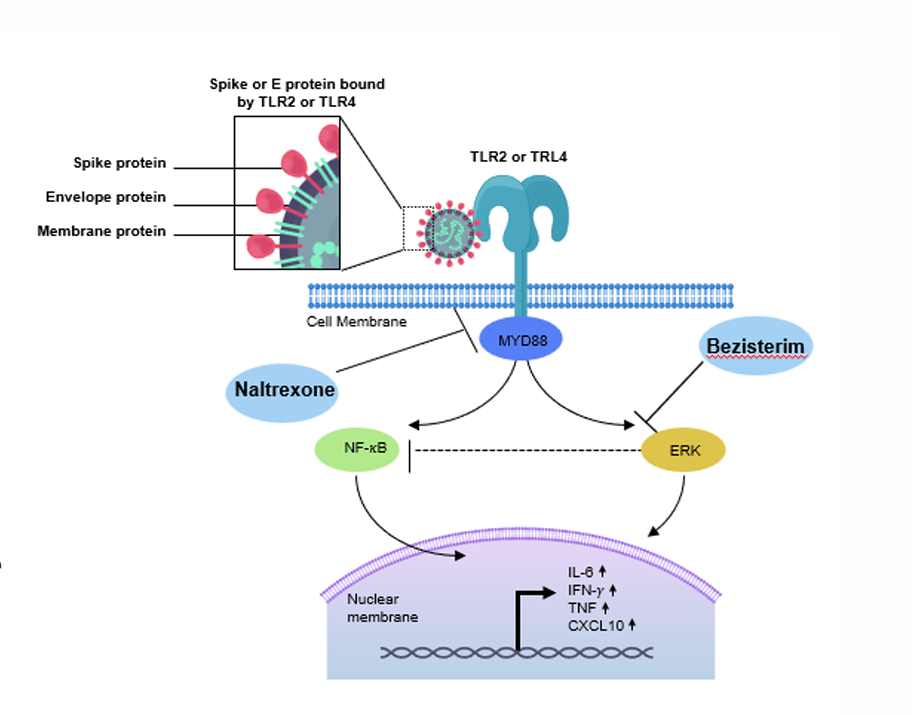
Notice how Bezisterim blocks “ERK” from telling the cells to produce TNFa and other proinflammatory cytokines.
TLR-4 upregulation has been implicated in long COVID, and studies suggest that a subset of ME/CFS patients may have elevated TNF-α levels. Bezisterim’s ability to reduce insulin resistance is another potential benefit given recent findings in ME/CFS and long COVID.
Bezisterim is the first TLR4-affecting drug to be trialed in these diseases. Note that the first illnesses BioVie trialed Bezisterim in (Parkinson’s, Alzheimer’s) involve neuroinflammation, which may play a key role in ME/CFS and long COVID.
A Different Kind of Trial – An Exploratory Long-COVID Trial
This trial was a little bit different. Most clinical trials aim for a single endpoint, like a pain or fatigue score, or a biological measure they need to hit for the trial to be declared a success.
BioVie entered the trial, though, recognizing that it didn’t know enough about long COVID to have a single endpoint. The disease is just too heterogeneous to do that right now, said Joseph Palumbo, MD, BioVie’s EVP of Research & Development and Chief Medical Officer:
“Research has demonstrated that Long COVID is not a single disease, but a complex and heterogeneous syndrome with multiple clinical and biological subtypes. A key challenge in clinical development is not only establishing efficacy but also identifying the patients most likely to benefit and understanding the drivers of that response.”
Subsets

BioVie used this trial to identify subsets it could target in a larger, phase 3 trial.
Instead of a single endpoint, BioVie assessed 22 different clinical outcomes. It also broke the patient population down into subsets (high fatigue, high PEM, high cognitive issues, high scores in more than one group).
The subgroup criteria are important. If I understand correctly, BioVie entered the trial with predetermined subgroup criteria; i.e., meeting a certain score or the median.
High Fatigue Group: BioVie determined that everyone with a score equal to or higher than the median (the exact middle score) would be in the higher fatigue group. The median PROMIS Fatigue score was 65, which means the healthiest person in the high fatigue group would experience something like this:
“I can shower, make breakfast, work or run errands, but I have to ration what I do; after a few hours I am markedly worn down, and doing several demanding things in one day is difficult.”
“Fatigue is present often enough and strongly enough to interfere meaningfully with getting things done, physical activity, sustained concentration, and social activity, but it does not by itself imply severe incapacity or inability to perform basic activities.”
This suggests that most people in the trial probably experienced significant fatigue.
High Post-Exertional Malaise Group – people in the top third PEM score. That ended up equaling DSQ-PEM ≥67.5. This is a little less clear but denoted people whose symptoms probably worsen quite substantially and repeatedly in response to exertion, and are among the most PEM-affected third of an already PEM-heavy long-COVID cohort.
Note that 90% of the study met the DSQ-PEM criteria. So virtually everyone in the study experienced significant PEM. The high PEM group simply had more PEM.
High Cognition Issues Group – equal to or above the median score (Cogstate Global Z ≤−0.108) – A Cogstate Global Z ≤−0.108 is not a particularly low score, which suggests that at least according to this test, people at the cutoff point were not noticeably cognitively impaired.
Biomarkers
| This was the most interesting part, and perhaps the most crucial part of the trial to me. To uncover biomarkers, identify subsets, and understand what the heck is happening in long COVID, the study included 400 markers of inflammation/immunity, neuroinflammation, neurodegeneration, proteomics, metabolic dysfunction, and DNA methylation (epigenetics). |
Essentially, the phase II trial was designed to pluck out specific long-COVID biological or symptomatic subsets that BioVie could successfully target in a big phase III study.
“Topline” Results
And now we have the “topline”, or early, results. The topline results contain the main statistical results. We didn’t get any of the biomarker results.
Not for Everyone
While some clinical endpoints trended toward significance, none of the 22 assessed were significant for the entire group. While this may sound bad, this is not really a surprise in a heterogeneous disease group. Steve Gardner of PrecisionLife believes it would be quite unusual for any drug to have success in an undifferentiated long-COVID or ME/CFS population. PrecisionLife’s genetic results alone suggest that the population is highly heterogeneous, and that different mechanisms drive the illness in different subsets.
For instance, PrecisionLife’s data suggest that inflammation/autoimmunity is a driver in a key subset of long COVID, but at least five other, often overlapping, drivers exist.
There is an interesting addendum, though. BioVie argues that although none of the 22 endpoints reached statistical significance, almost all trended in the right direction.
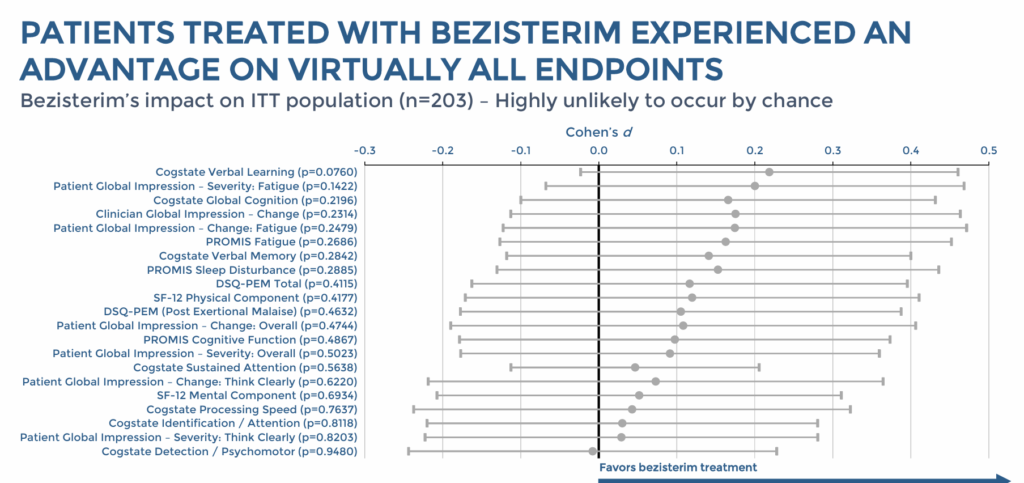
Better Luck with Subsets
When BioVie broke the long-COVID group down into 4 symptom subsets, Bezisterim appeared to do much better. While it didn’t blow the socks off any group, it did produce broader and more consistent results than we’ve seen before.
Note that if I’m reading this correctly, because BioVie gave us Cohen’s d effect sizes but not the underlying changes in scores, we don’t yet know Bezisterim’s absolute effect—i.e., specifically how many points it improved fatigue or cognition compared with placebo.
Cohen’s d instead expresses the average difference between the Bezisterim and placebo groups relative to the variability in those scores. Where Bezisterim showed an effect, the standardized differences were generally moderate. That suggests a real, noticeable group-level effect, but it does not, by itself, tell us how clinically meaningful the improvement was or what proportion of patients benefited substantially.
The High PEM group (about 1/3rd of the participants): Bezisterim improved processing speed (key cognitive finding in ME/CFS), “global cognition,” clinician global improvement, patient global improvement, attention, PEM, and fatigue. A couple of other cognitive assessments came pretty close to significance. This drug, then, appeared to affect a broad array of symptoms. However, physical functioning and other symptoms did not improve significantly.
The Worsened Cognition Group (about 1/2 of the participants) significantly improved their scores on four cognitive domains (verbal learning, global cognition, verbal memory, processing speed) – a nice broad finding. Note that most objective fatigue, PEM, and quality-of-life measures did not significantly improve.
The Higher Fatigue Group (about 1/2 of the group): Again, we see the drug affect a broad array of fatigue measures, including PGI fatigue severity, PROMIS fatigue, PGI fatigue change, clinician global change, and PGI overall change scores. PEM and sleep scores improved but did not reach significance.
These also appear to be moderate-size effects, but as noted, we don’t have the absolute results; i.e., we don’t appear to know exactly how much these scores changed or how clinically impactful they were.
Conclusion – while the results appeared moderate, they also appeared broad; i.e., they appeared to impact a wide range of symptoms across the different groups. The drug’s ability to moderately improve fatigue, cognition, attention, global change, and PEM (in 2 groups) suggested it was having an impact.
Response
People involved in the study were happy with the results.

Penelope Markham PhD has a family member with ME/CFS.
Penelope Markham, leader of BioVie’s long-COVID team, stated:
“We think it’s fantastic data, we are very excited, and we will pursue Breakthrough Therapy designation,” (A Breakthrough Therapy designation from the FDA allows a phase III trial to proceed more rapidly.)
Cuong Do, president and chief executive officer of BioVie, said:
“To our knowledge, this is the first time a drug candidate has shown the ability to help patients improve across these persistent long-COVID symptoms,”
Ezra Spier, a long-COVID patient-researcher who’s been in the thick of clinical trials, stated:
“What really stands out to me about the data that have been presented today is that it shows a very clear direction toward improving key symptoms. It gives the community some hope, because we’ve been seeing trial fail after fail after fail. Seeing something that provides demonstrated impact, I think is really exciting.”
”Michael Peluso, UCSF long-COVID researcher and LIINC cofounder, who advised BioVie on the trial:
“There have been, at this point, a few dozen Long COVID trials of other agents, and really none of those have had results that are as consistent and as compelling as what I’m seeing here.”
Clues from the Parkinson’s and Alzheimer’s Trials
Bezisterim tamped down both neuroinflammation and systemic inflammation in Parkinson’s patients.
The Parkinson’s disease trial was much smaller but showed an interesting potential coherence with the long-COVID results, as the Parkinson’s patients with elevated inflammatory biomarkers at baseline did the best. The drug also produced broad reductions in neuro‑ and systemic‑inflammation biomarkers; i.e., it reduced both neuroinflammation and inflammation in general.
BioVie is now attempting to run a phase III trial focused on early Parkinson’s patients with elevated inflammatory markers.
A small (n=20) phase II Alzheimer’s study found the drug improved cerebral blood flow and functional connectivity, as well as several tau biomarkers. A 439-person, phase III study has been completed, but topline results have not been shared yet.
A Long-COVID Helper? Not a Long-COVID Killer
Thus far, we just have general subset scores. While people associated with the trial (Peluso, Do, Spier, Markham) were quite positive, none of them portrayed the drug as a long-COVID killer.
Right now, Bezisterim more looks like a potential “long-COVID” mover than a long-COVID killer. Spier said the drug “shows a very clear direction toward improving key symptoms”. Peluso’s exclamation that no other trial results have been “as consistent and as compelling” stands next to the underwhelming trial results thus far.
The drug’s ability to produce moderate effects across multiple symptom domains in people with more severe long COVID is more than we can say about any other long-COVID drug to date. This suggests that if you gave the drug to a person experiencing high fatigue who had long COVID, you’d have a moderate chance that that person would experience significant improvement.
Moving Forward
Ultimately, the trial was too small to tell us how effective Bezisterim was. Until we have the full results, we won’t know how clinically meaningful these treatment effects are. We know the drug had a “moderate treatment effect”; that BioVie had a moderate chance of knowing who got the drug simply by looking at their scores at the end of the trial.

What will happen when BioVie adds in the biomarker results?
A drug that could zero in on an illness would have a high treatment effect score; i.e., everyone who got the drug would improve. A drug that made little difference would have a low treatment effect score. Bezisterim was in the middle – not great but not terrible either.
That was when BioVie focused on predetermined (not necessarily optimal) symptom subsets. Remember that this trial was not designed to provide the final word on Bezisterim: it was designed to identify a subset or subsets that BioVie could target in a larger, phase III trial.
The really interesting question for me is what happens when BioVie adds in the biomarker results. Will it be able to pluck out an inflammatory subset that had a high effect score; i.e., it significantly helped virtually everyone in that group?
Note that, in Peluso’s view, Bezisterim doesn’t have to be a breakthrough drug to succeed; it just has to be successful enough to give drug companies the confidence to take a chance on long COVID. For instance, if drug companies saw that reducing an inflammatory marker with Bezisterim could affect fatigue, PEM, or cognitive scores, that might be very interesting to them, given the scores of anti-inflammatory drugs out there.
Honestly, I would be surprised if anyone happened on a long-COVID “killer” at this point. The best we can probably hope for in this second generation of trials is treatments that are helpful for a significant subset of people and perhaps quite helpful for a more selective subset.
It will probably take the “third generation” of clinical trials which specifically target biologically coherent subsets to get dramatic across-the-board improvements. If BioVie can biologically identify a subset of patients with X levels of inflammation whose cognitive scores, fatigue, PEM, etc., improve dramatically, that would fit the bill.
BioVie reported that 12/12 of its investigators and advisors, including David Putrino, Hannah Davis, Maureen Hanson, Timothy Henrich, and others, supported moving to the conclusive phase III trials. It believes the trial provided enough evidence to move forward with a larger phase III trial and is meeting with the FDA.





It will be interesting to learn whether the researchers believe permanent gains (or recuperations) can be made from this biologic, or whether users will need a lifetime Rx just to stay above water. Or, better yet, if they think combining it with some other intervention or therapy would open the door to actual recovery.
As someone who usually stops taking almost anything the medical profession offers due to SIDE EFFECTS, I’m wondering what the side effects are for this drug to produce its modest results, and whether the small improvements are worth the side effects.
If it was a cure, we’d learn to deal with the side effects somehow; so I’ll be watching this along with all the other things which help ‘a bit’, but will have to depend on test subjects who are sturdier than I am and can tolerate the cost to their bodies of taking a drug.
Looked good. More side effects in the placebo group.
yep – looked fine
the key question is how significant the improvements are, and in particular sub-groups.
One note of caution is that the company behind the drug are quite effusive – there’s obviously some bias in that respect. Countering that, however, is Putrino’s relative positivity. Involved in the study, but not the company!
It’s nice to have a positive outcome, even if there’s still plenty of questions
Whenever I see a potential new drug, my hopes briefly go up and then dropped suddenly when I think about myself and the huge number of people with ME/CFS develop medication intolerance.
Even drugs we used to tolerate can become intolerable after stopping them for a few months, as if the body has “forgotten” the molecule. Yet had we not stopped, we could’ve remained on that particular medication.
But mostly occurs with brand new molecule our bodies have never seen before so not IgE mediated. Yet the body still sends out an alert sickness response occurs even on the tiniest of doses (not PEM, however can be so stressful on the body, it can later trigger PEM)
This means many patients can’t access potentially useful treatments, often not even antibiotics or other important medicines. For example I cannot take much needed statins.
I know this response can be switched off because I’ve taken several medications I normally cannot tolerate alongside a glucocorticoid, and it completely blocked my usual reaction. I could take the medication easily, with none of the usual intolerance side effects.
Steroids are absolutely not the solution. They’re far too broad and hard on people with ME/CFS. But that response is a pretty impressive clue that there may be a specific mechanism researchers could target.
If researchers don’t investigate medication intolerance, we risk developing treatments that a huge proportion of people with ME/CFS simply can’t take.
Thank u !….this.! … your last2 sentences. It is so frustrating, huh
Yes!!! This is so true and its costs our hope! Every medicine that vasodilition brings, drives my Tinnitus crazy, even supplements.
I am the same way, highly reactive to almost all medication. But I would think that, if there is a treatment that gets to the core physiological issue, that we should be able to tolerate it, because it would resolve the very problem that is causing the hypersensitivity in the first place. Or am I being naïve here?
Yes, We may eventually find a miracle treatment that gets to the underlying mechanism of ME/CFS and switches it off. If that happens, I would expect the medication-intolerance problem to resolve too. But the problem is the period between starting that treatment and it actually becoming therapeutic.
As many people with ME/CFS may not be able to tolerate a new wonder drug treatment for long enough to reach that point.
That’s why I think we need something that can temporarily block the sickness response and that awful poisoned, flu-like feeling that many of us experience when we take new medications.
Glucocorticoids can be very effective at reducing this reaction for some people, but they can also worsen ME/CFS so are not a solution for medication intolerance. Especially if a new wonder drug has to be taken for a long time before it becomes therapeutic.
And worse still if it is an ongoing medication we have to take. Although hopefully when it becomes therapeutic for medication and intolerance goes away
What we need is something that dampens medication intolerance without overdriving whatever underlying cellular or immune processes contribute to PEM and deterioration that glucocorticoids can cause.
In other words, we need a “bridge”. Something that allows people to tolerate a potentially disease-rectifying treatment long enough for it to start working. Otherwise, the very medication intolerance we have could prevent us from ever reaching the treatment that might solve it
It’s a classic catch 22 situation
However, I do believe there may eventually be a drug that can block medication intolerance. If glucocorticoids can suppress the reaction, then there must be some part of the underlying mechanism that can potentially be targeted more narrowly, without the broad effects of steroids. I suspect it could involve one or more of the pathways behind the sickness response, such as inflammatory cytokines or prostaglandins, but it could also involve neural signalling between the body and brain. The area postrema is one possible part of this system because it detects circulating signals from the body and communicates with brainstem circuits involved in sickness responses.
Interestingly, diclofenac has also partially reduced my medication intolerance. Because it blocks COX enzymes and reduces prostaglandins, this makes that pathway particularly interesting to me. In my case, taking diclofenac alongside a glucocorticoid allowed me to reduce the steroid dose by about half. It’s only an observation from my own experience, but I think it’s worth investigating.
I tend to believe that many of our symptoms are side effects of protective (Dauer / inhibition) mechanisms. Taking (too high doses of) a medication that tries to alleviate symptoms then risks to reduce the protective effect and our bodies might react to it.
Even if one does not share this view, many of us will have taken multiple drugs with severe side effects *that are typical for that particular drug* and hence not likely due to medication intolerance but to an actual known side effect of that medicine.
Any severe reaction, especially if the drug is ‘hitting’ for example the gut locally hard when the cap is opening, has a real risk to create a fairly bad local situation that is not so much different from a severe local inflammation. That in turn creates a severe risk for the immune system to kick in and try and identify / tag / counter / neutralize… the offending chemical / drug (either by antibodies or innate immune system or…).
Now imagine having at different times in the past taken 10 rather different medications that gave all strong averse reactions that triggered the immune system to kick in. It’ll have tried to identify and oppose the offending substances. Now each time that is the particular drug and the other stuff in those pills. If for example each time that pill included one common component (for example methylcellulose), then it’s not that far a stretch for the immune system to ‘put that on the bad list’ too. Eg form antibodies or another form of immunity aggainst it.
That idea sort of is observed in https://pmc.ncbi.nlm.nih.gov/articles/PMC8355062/
Tittle
“Hidden Dangers: Recognizing Excipients as Potential Causes of Drug and Vaccine Hypersensitivity Reactions”
Quote
“Suspicion for these “hidden dangers” should be high in particular when anaphylaxis has occurred in association with multiple chemically distinct drugs. Common excipients implicated include gelatin, carboxymethylcellulose (CMC), polyethylene glycols (PEG) and products related to PEG in immediate hypersensitivity reactions (IHRs); and propylene glycol (PG), in delayed hypersensitivity reactions (DHRs)”
It doesn’t say directly that it happens due to “multiple unrelated failed experiments” but it says it happens. It describes the case of patients getting severe reactions to something as ‘benign’ as the empty capsule itself.
That’s one of the reasons why I try and avoid to test everything that commes along and be conservative at dosing for anything that doesn’t require full dosing (remember that some medications like antibiotics need to be taken at prescribed dose for the full length of time!). A few failures in my experience can undo years of slow progress. This is but one way to have that. And once you react strongly to the pill’s packaging, chances IMO are (increased) that the immune system will also react to the new drug in it…
When I was first diagnosed with Immune Deficiency and Chronic Encephalopathy (CFS wasn’t even a diagnostic name then) in the early 1980’s, my first symptoms were tinnitus, horrible headaches, reactions to drugs “, chemicals” and foods. I also had constant infections and reactions to the antibiotics used to treat them and overwhelming fatigue…like a cement truck had suddenly dumped a load of cement on me.
The two research immunologists who diagnosed me put me on an orphan drug from Germany, a form of heparin in pill form. This helped with the chemical sensitivity. But, I still have drug reactions, most recently from Advil used to treat a wrist fracture. My fingertips started to peel off and now I can’t take a NSAID anymore.
Chemical sensitivity goes way beyond just medications and it existed long before ME/CFS and Long Covid. There were treatment centers with white rooms where you were not exposed to any chemical and patients did improve. Unfortunately we don’t live in this kind of environment.
Even more troubling is that we store many lipophilic chemicals in our body fat and certain activities can make them come out into the bloodstream where they can create havoc.
I am puzzled about why no studies have been done on this potential cause of ME/CFS and PEM.
Agreed – I don’t know why some things are figured out, and others, like this bunch of symptoms we share with Long Covid, just continue to be puzzles no one can solve.
Knowledge will probably come too late for me to benefit much (I’m 77), but it would be nice to know what the heck has happened to us. And of course the world needs the Long Covid crowd to get well and back to work/life.
Very important is the question of who is actually able to tolerate the physical cost of taking a drug. Trial participants may be considerably sturdier than I am and better able to tolerate adverse effects or other stresses a medication places on the body.
In the research trials I have read so far, I have not seen enough attention paid to participants’ pre-existing conditions and how those conditions might affect drug tolerability.
This is particularly important in my own case. Because I have post-polio syndrome (PPS), there are several medications I need to avoid altogether or take only at substantially reduced doses.
A drug that appears reasonably well tolerated in a clinical trial population may therefore carry very different risks for someone with significant pre-existing vulnerabilities.
For patients like me, the question is not simply whether a drug works, but whether our bodies can safely tolerate the cost of taking it.
Cautious optimism!
On the TDR-4 front, I note urolithin A has shown some inhibitory effects. Given this, and it’s impact on mitochondria, I am going to give it a try. Not cheap though!
And red light therapy
The 12-week duration of the trial is fairly short in my opinion for long covid. When the body is really run down it takes many months to recover. It would be really interesting to see results over 6 to 12 months. Hopefully there would be an even greater response, or at worst sustained.
This is a good point, especially since the drug seems to operate on a number of pathways.
I will say it again: Long-Covid is NOT ME/CFS/POTS/FM.
So these patiënts get nothing out of this trial.
Respectfully I would have to disagree. I think that Long Covid can be classed as a subtype of ME/CFS. Here in NZ a study supports this notion – https://www.otago.ac.nz/news/newsroom/strong-links-found-between-long-covid-and-mecfs-study
Long Covid can have some symptoms that are not generally found in those with ME/CFS, however, the immunological cascade appears to be similar.
I wouldn’t say it’s a subtype. Rather, I think the illnesses are related and overlap, but are different.
A recent study found different aspects of a variety of illnesses, but shared / overlapping pathways. This is quite plausible. The illnesses studies included ME/CFS, long covid, MS, POTS.
It’s possible, but not at all certain, that bezisterim could potentially offer more benefit for ME/CFS than long covid.
Leapy 99, Have you had both ME/CFS and Long Covid? ME/CFS symptoms (no name then) diagnosed in the early 1980’s and Covid in 2023 and again 8 months later in 2024. ME/CFS is bad, but Long Covid is worse. One month after the first Covid, my heart and blood pressure went haywire. A fine cardiologist worked to settle this down. Then one month after Covid in 2024, I lost my ability to walk without a cane. My balance was shot and I haven’t been able to get it back. They call it “Covid Gait”.I have had 3 falls since then. These symptoms were not part of the serious case of ME/CFS I had for nearly 40 years before this. I was originally diagnosed by two immunologists and then treated by Dr. Paul Cheney until he retired. I had some bad times, but on balance, they were nothing to what I am experiencing now with Long Covid. ME/CFS may make you more vulnerable to getting Long Covid, but they are not the same thing.
Betty, I’ve been having episodes of post- viral illnesses since I was six years old. They’ve all been different with regard to severity of symptoms, but I’m certain they’re all due to the same disorder. My age and health at the time likely contributed to how the illnesses presented, and I see how this could make them seem like different diseases. I believe I likely have a genetic predisposition, or even a genetic abnormality, that contributes to or causes these illnesses.
For me, Long Covid was the second worse illness, but it’s still been severe. The worst ME/CFS I experienced began in 1996. I was fortunate enough to find a neuroimmunologist to treat me at MUSC. He immediately knew what I had and sent me for tilt table testing, which I failed, and was also diagnosed with POTS. Additionally, I’ve had FM since I was 18.
Both in ’96 and with Long Covid I had significant balance issues. My proprioception was whacked. I was constantly falling, banging into door jams, misjudging distances, and dropping things. My doc in ’96 put me on pentoxifylline and it resolved all my balance issues. I took it again for Long Covid, and it’s been like a miracle drug – it’s cured at least a dozen of my symptoms. It’s an off-label use, but it has immune-modulating properties and has been used to treat a number of auto-immune disorders. It’s a safe drug with few side effects. I’m surprised it’s not been trialed for LC.
Chronic inflammation plays a role in every disease you mentioned, and in many more. So this drug can be helpful in many different diseases. The question is, how helpful it will be and will the effects last.
Even if LC is different in some ways from ME/CFS/POTS/FM, you could also argue that ME-CFS is a pathological homeostasis and that LC is just one way to get to it.
Do you know how well progressed Patterson’s Maraviroc study is, Cort?
I am skeptical (because I doubt viruses perpetuate the illness), but always keep an open mind 🤔
Hi Matthias, You are always saying that you don’t think a virus is responsible for ME/CFS. (It certainly is for Long Covid). Why do you believe this so strongly?
Hi Betty, actually I never said that. I think a virus triggers many if not all cases of ME/CFS. I have always been clear on that.
I don’t think a virus perpetuates the illness. If I am right, then antivirals will have no benefit. And in fact, antivirals gave failed in every study so far in both ME/CFS and Long Covid.
I don’t know if you watched Dr Jay Chung’s webinar. He has exactly the same view as me.
I have been quite strong on this because I think an awful lot of time and money is still being wasted on this dead end theory. I think it has appeal because it’s simple, but the illness is clearly complex.
Hey, if I am proven wrong by one of these trials then I would be very happy! If viral reactivation is perpetuating the illness, and an antiviral succeeds, and people get better – brilliant!
But I doubt it
Don’t forget that antivirals can and do succeed in studies, but their effects are basically anti-inflammatory, not antiviral per se. Also don’t forget that EBV reactivation is strongly implicated in progression to a cell-danger response like PEM. But in the end, you’re probably right that viral remnants aren’t driving the inflammation.
Hi Matthias,
Not all antivirals treat all viruses. Maybe they are treating the wrong virus, one they are not testing for, but about which they have been well informed since at least 1986.
I don’t know where the Paterson study is currently, but I can say that the utility of Maraviroc is not as an antiviral per se, but rather as an anti-inflammatory + CCR5 (C-C chemokine receptor type 5) receptor antagonist. HIV studies showed it has the ability to reshape the receptors. Presumably through these actions the blood vessels (damaged by acute and ongoing inflammation) would be allowed to recover.
(…) Will it be able to identify an inflammatory subset that benefited significantly?”
I think this is the essential point
One should probably say ‘least worst” Long COVID trial instead of best, because this trial was very mid.
Heavily Marketing-hacked (science via press release), small effect sizes, and didn’t include moderate or severe patients.
Some of your cynicism is justified, especially the marketing angle.
Having said that, the researchers that were involved endorsed the study.
Further, it often seems that trials in long covid or ME/CFS elicit stronger effects in moderate or severe patients. So perhaps moderate gains in less severely affected patients is potentially quite promising?
Regarding the meaning of an effect size – it is about the size of the effect, rather than the chance of any given individual benefitting from the drug. A small effect size suggests people in the treatment group experienced, on average, a small (and possibly clinically insignificant) benefit, a large effect size suggests on average a big benefit, and a moderate effect size is somewhere in the middle.
Thanks for your great synthesis as always!
Thanks for the comment. I’ve modified the blog to encompass Cohen’s D more accurately 🙂
Dutch study just out showing no significant peripheral immunological differences between long covid patients and controls.
But didn’t look at immunology in the CNS. As I have said many times, that’s where I think the issue is.
https://www.nature.com/articles/s41598-026-73807-x?fromPaywallRec=false
“Many patients with LC who experience PEM adopt pacing strategies to avoid post-exertional symptom exacerbation, potentially stabilizing baseline physiology. Supporting this hypothesis, we previously demonstrated enhanced IFN-I bioactivity following RIG-I stimulation in blood mononuclear cells from the same individuals included in the present study [41]”
That may be a rather important part here. Cort’s previous blog reported on the hypothesis that mtDNA played a considerable role in ME/CFS https://www.healthrising.org/blog/2026/09/19/ivo-21-mitochondrial-drug-chronic-fatigue/.
I believe both mtRNA and mtDNA play a role. And RIG-I is a human antiviral gene that can stimulate IFN-I (interferron production, leading to itaconate production; related to itaconate shunt hypothesis): https://www.sciencedirect.com/science/article/pii/S0171298525002190
Title
“Mitochondrial RNA/RIG-I promotes Caspase-1/GSDMD-mediated inflammation in sepsis-associated acute kidney injury”
And https://www.nature.com/articles/s42255-024-01145-1
Title
“Itaconate drives mtRNA-mediated type I interferon production through inhibition of succinate dehydrogenase”
=> IFN-I can promote itaconate production and itaconate production does drive mtRNA-mediated IFN-I production = another potential vicious circle (and close to confirmation).
Note: Dr. Phair started in his youtube video discussing the itaconate shunt from the (back then) unpublished observation that there was a modest but significant increase of type I interferon production in ME/CFS and that should stimulate itaconate production. The nature paper you linked provides proof of that, but after exertion.
Correction, *this* reference speaks of increased IFN-I production in LC:
Humer, B. et al. Exaggerated IFN-I response in long COVID PBMCs following exposure to viral mimics. J. Clin.
Immunol
Then if / when Dr. Phairs reference to unpublished work of another ME/CFS researcher he talked about is confirmed, then this could be a common mechanism between ME/CFS and LC.
Bezisterim’s results should be viewed as hypothesis-generating until they are prospectively confirmed in a larger clinical trial.